

THE FIRST TREATMENT APPROVED FOR CKD ASSOCIATED WITH T1D IN 30+ YEARS1,2
Efficacy & Safety
THE FIRST TREATMENT APPROVED FOR YOUR ADULT PATIENTS WITH CKD ASSOCIATED WITH T1D IN 30+ YEARS1,2
KERENDIA reduces UACR, which is expected to slow CKD progression1,3
In FINE-ONE (N=242), a phase 3, randomized, double-blind, placebo-controlled trial, the efficacy and safety of KERENDIA were evaluated when added to a stable dose of an ACEi or ARB in adults with CKD associated with T1D.1,3
EFFICACY
In adult patients with CKD associated with T1D
KERENDIA significantly reduced UACR vs placebo over 6 months on top of standard of care1,3*
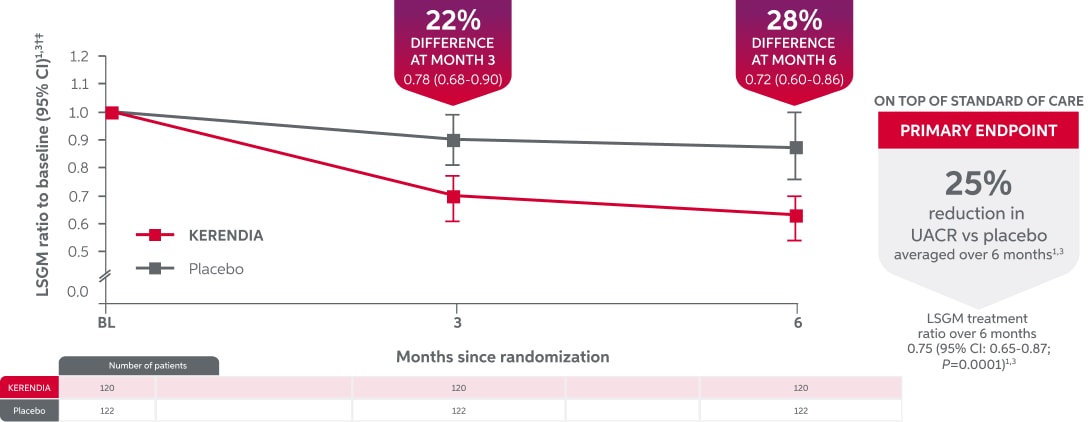
The adjusted relative reduction in UACR comparing KERENDIA with placebo at Months 3 and 6 were exploratory endpoints. Confidence intervals are unadjusted and should not be used for inference.3
Reductions in UACR were observed as early as Month 3 and were sustained through Month 61
*Patients were required to be taking a stable dose of an ACEi or ARB as standard of care.1
†Figure adapted from Heerspink HJL, et al. N Engl J Med. 2026.3
‡Up to 3 daily UACR measures were combined into a geometric mean UACR prior to the analysis of the ratio to baseline of geometric mean UACR.3
ACEi=angiotensin-converting enzyme inhibitor; ARB=angiotensin receptor blocker; BL=baseline; CI=confidence interval; CKD=chronic kidney disease; LSGM=least-squares geometric mean; T1D=type 1 diabetes; UACR=urine albumin-to-creatinine ratio.
SAFETY
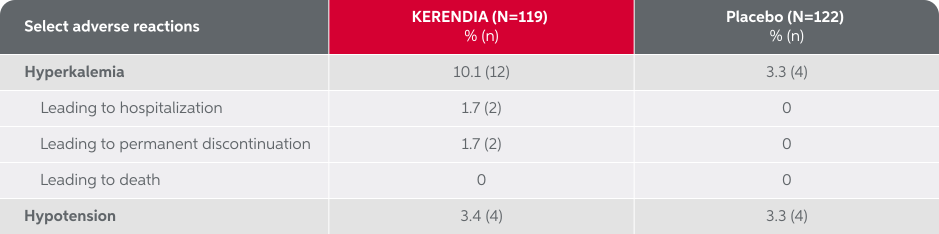
KERENDIA was generally well-tolerated in adults with CKD associated with T1D1
The overall safety profile of KERENDIA in the FINE-ONE study was consistent with the adverse reactions reported in patients with CKD associated with T2D.1
Select adverse reactions in FINE-ONE3,4
Adverse reactions in patients with CKD associated with T2D1
From the pooled data of FIDELIO-DKD and FIGARO-DKD, the adverse reactions reported in ≥1% of patients on KERENDIA and more frequently than placebo were hyperkalemia (14% vs 6.9%), hypotension (4.6% vs 3%), and hyponatremia (1.3% vs 0.7%).
CKD=chronic kidney disease; T1D=type 1 diabetes; T2D=type 2 diabetes.
INDICATIONS:
KERENDIA (finerenone) 10 mg, 20 mg tablets is indicated to:
- reduce the risk of sustained estimated glomerular filtration rate (eGFR) decline, end-stage kidney disease, cardiovascular death, non-fatal myocardial infarction, and hospitalization for heart failure in adult patients with chronic kidney disease (CKD) associated with Type 2 diabetes (T2D)
- reduce urinary albumin-to-creatinine ratio (UACR), which is expected to reduce the risk of sustained estimated glomerular filtration rate (eGFR) decline and end-stage kidney disease in adults with CKD associated with Type 1 diabetes (T1D)
IMPORTANT SAFETY INFORMATION
CONTRAINDICATIONS:
- Hypersensitivity to any component of this product
- Concomitant use with strong CYP3A4 inhibitors
- Patients with adrenal insufficiency
WARNINGS AND PRECAUTIONS:
Hyperkalemia: KERENDIA can cause hyperkalemia. The risk for developing hyperkalemia increases with decreasing kidney function and is greater in patients with higher baseline potassium levels or other risk factors for hyperkalemia. Measure serum potassium and eGFR in all patients before initiation of treatment with KERENDIA and dose accordingly. Do not initiate KERENDIA if serum potassium is >5 mEq/L.
Measure serum potassium periodically during treatment with KERENDIA and adjust dose accordingly. More frequent monitoring may be necessary for patients at risk for hyperkalemia, including those on concomitant medications that impair potassium excretion or increase serum potassium.
MOST COMMON ADVERSE REACTIONS:
- The adverse reactions reported in ≥1% of patients on KERENDIA and more frequently than placebo were hyperkalemia (14% vs 6.9%), hypotension (4.6% vs 3%), and hyponatremia (1.3% vs 0.7%).
DRUG INTERACTIONS for KERENDIA 10 mg, 20 mg:
- Strong CYP3A4 Inhibitors: Concomitant use of KERENDIA with strong CYP3A4 inhibitors is contraindicated. Avoid concomitant intake of grapefruit or grapefruit juice.
- Moderate and Weak CYP3A4 Inhibitors: Monitor serum potassium during drug initiation or dosage adjustment of either KERENDIA or the moderate or weak CYP3A4 inhibitor, and adjust KERENDIA dosage as appropriate.
- Strong and Moderate CYP3A4 Inducers: Avoid concomitant use of KERENDIA with strong or moderate CYP3A4 inducers.
USE IN SPECIFIC POPULATIONS:
- Lactation: Avoid breastfeeding during treatment with KERENDIA and for 1 day after treatment.
- Hepatic Impairment: Avoid use of KERENDIA in patients with severe hepatic impairment (Child Pugh C) and consider additional serum potassium monitoring with moderate hepatic impairment (Child Pugh B).
Please see the full Prescribing Information for KERENDIA.
